
Chronic inflammatory demyelinating polyneuropathy is a progressive motor and sensory neuropathy that is very painful and debilitating, caused by damage to the covering of the nerves (myelin). For VA disability purposes, CIDP has no diagnostic code of its own, so VA generally evaluates the affected peripheral nerves and the functional loss in each extremity.
CIDP is not an easy case to win at the VA. It is not a presumptive disease and you have to fight to get it service connected. You will likely need an expert opinion to link the disease to a type of toxic exposure.
How Does CIDP Affect Veterans?
Chronic inflammatory demyelinating polyneuropathy is characterized by gradually increasing sensory loss and weakness associated with the loss of deep tendon reflex in the legs and arms. The hallmark of a peripheral nerve disease is loss of ankle reflex. This is when your doctor hits your Achilles tendon and there is no reflex.
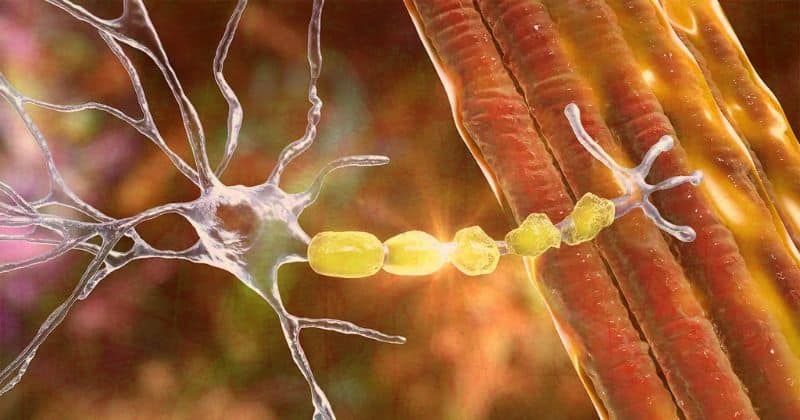
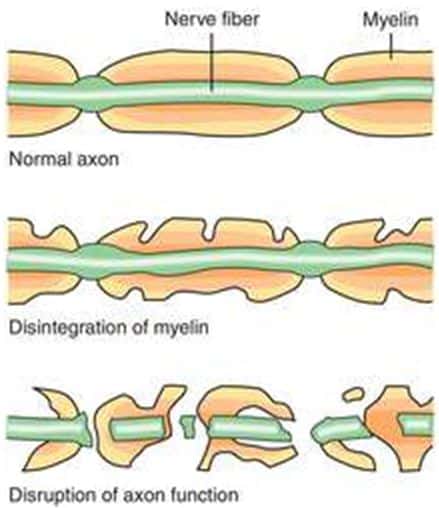
The axon (nerve fiber) works like an electric wire. The myelin sheath around the axon is the insulation necessary for the nerve to conduct electrical impulses properly. In CIDP, myelin is attacked through very complex mechanisms. In such cases, the body sees the peripheral nerve as foreign and antibodies bind to the myelin and begin to break it down.
For example, if you want to move your finger, messages tell your brain to move the finger. Then electrical communication within your body tells your nerves and muscles to move the finger. When there is disruption in the myelin sheath, those messages are weakened. Your brain is telling your finger to move but the nerves are damaged and the movement is weakened, delayed, or absent. When the myelin sheath is completely damaged, the message is blocked and this is called paralysis.
Because it is a gradually progressing disorder and its symptoms may, at early stages, wax and wane, a definitive diagnosis may require invasive tests. However, a neurologist that has experience in this type of disease should be able to identify the gradual symptoms and rule out any other cause.
What Are the Symptoms of CIDP?
The typical symptom of the disease is weakness, manifested in daily living activities. Someone might find they cannot get off the toilet, stand up out of a chair, or get out of the car easily. Arm weakness leads to inability to hold things, difficulty carrying items, or trouble putting the plates on the shelves. Fine motor skills get impaired. People begin to notice a change in handwriting and they can’t zip up zippers. Women may have difficulty putting on their earrings.
For VA purposes, CIDP ratings depend on the functional loss caused by the neurological disease. The medical records should show how the veteran is affected by weakness, fatigue, sensory loss, reflex changes, difficulty walking (including altered gait or stumbling), and loss of hand or foot function.
CIDP vs. Guillain-Barré Syndrome
CIDP is closely related to Guillain-Barré syndrome (GBS) and it is considered the chronic counterpart of that acute disease. Current neurology literature distinguishes GBS as generally acute and monophasic, while CIDP has a chronic or relapsing course and a progressive phase that lasts more than two months. Acute-onset CIDP can initially resemble GBS.
A 2024 review reported that no diagnostic biomarker reliably detects CIDP or Guillain-Barre syndrome, so diagnosis depends on integrating clinical characteristics and supportive data. That is one reason VA claims involving CIDP may need careful medical evidence when VA points to a competing diagnosis.
For a VA claim, an accurate diagnosis helps identify the affected nerves, extremities and functional loss. A prior GBS diagnosis, treatment-related fluctuation or another neuropathy label may require a neurologist to explain how the veteran’s later CIDP diagnosis fits the clinical history.
Learn How To File And Win Your VA Claim
Get our FREE book The Road to VA Compensation Benefits.
get the free book
What If a Veteran Has CIDP and Another Neuropathy Diagnosis?
A veteran with CIDP may also have diabetic neuropathy, idiopathic peripheral neuropathy, radiculopathy, carpal tunnel syndrome or another nerve diagnosis. Idiopathic (“of unknown cause”) means that doctors cannot find a cause or root of the neuropathy. Because patients may have subtle pain or weakness, it may be difficult to arrive at a specific diagnosis of toxic neuropathy at onset.
CIDP is often misdiagnosed as idiopathic peripheral neuropathy. Doctors also delay its diagnosis by associating it with getting old, a patient being deconditioned, spinal stenosis or some other problem.
If medical professionals cannot distinguish which symptoms belong to CIDP and which symptoms belong to another neuropathy, the determination of service connection and the rating should reflect that uncertainty rather than assigning symptoms away from the service-connected disability without explanation.
For example, in Board decision No. 23058221, the Board addressed overlapping idiopathic peripheral neuropathy symptoms that medical evidence could not separate from the veteran’s service-connected CIDP. That kind of factual issue can be decisive in a complex neurological appeal.
How to Service Connect CIDP
Veterans can get CIDP service connected through direct service connection, the chronic disease rules for organic diseases of the nervous system, or secondary service connection. The right theory depends on the veteran’s service history, symptom timing, exposure history and already service-connected disabilities.
Direct Service Connection for CIDP
Direct service connection is often the main route for CIDP. Under 38 C.F.R. § 3.303(d), VA can grant service connection for a disease diagnosed after discharge when the evidence establishes that the disease was incurred in service. A direct CIDP claim requires a current CIDP diagnosis, an in-service event (injury, disease or exposure) and a medical link connecting the two.
Learn how to make a Va claimCan Agent Orange Exposure Support a CIDP Claim?
CIDP is not an Agent Orange presumptive condition, but a veteran with qualifying herbicide exposure may still pursue direct service connection. Presumed exposure can establish the in-service exposure element, while medical evidence must address whether that exposure caused or contributed to the veteran’s CIDP. Hill & Ponton’s guide to Agent Orange and CIDP VA Disability Claims explains the herbicide-specific science, delayed-onset issues, nexus opinions and Board decisions.
CIDP as an Organic Disease of the Nervous System
VA recognizes certain organic diseases of the nervous system as chronic diseases under 38 C.F.R. § 3.309(a). According to 38 C.F.R. § 3.307(a)(3), a qualifying chronic neurological disease may be presumed service connected when it becomes manifest to a compensable degree within one year after separation.
Weakness, numbness, gait problems, reflex changes or other neurological symptoms documented during the first year after discharge may support this theory even if the CIDP diagnosis came later.
Early medical records can be critical. Service treatment records, separation records, emergency-room notes, private neurology records, physical therapy records and lay statements may help show when the neurological disease first became visible.
VA’s adjudication guidance includes peripheral nerve conditions within the broader category of organic diseases of the nervous system and directs adjudicators to seek guidance when the classification of a particular diagnosis is uncertain.
Secondary Service Connection for CIDP
VA may grant secondary service connection when a service-connected disability causes or aggravates another disability. A secondary CIDP claim requires medical evidence explaining the relationship and, once CIDP is service connected, additional disabilities caused or aggravated by CIDP may also qualify.
Secondary claims involving CIDP often require care because diabetes, radiculopathy and other nerve diagnoses can overlap. The medical opinion should explain what can be separated and what cannot be separated medically.
How Does VA Rate CIDP?
Because VA has no diagnostic code specifically for CIDP, it evaluates the neurological impairment under the peripheral nerve code or codes that best describe the affected nerve distribution. It may also rate CIDP by analogy when the rating schedule does not name the diagnosed condition.
The peripheral nerve schedule rates impairment by comparison with mild, moderate, severe or complete paralysis of the affected nerve. VA must also consider impairment of motor, sensory or mental function, including partial loss of use of extremities, disturbances of gait and other neurological manifestations.
Selected Peripheral Nerve Codes Used in CIDP Ratings
| Diagnostic Code | Nerve or Group | Mild | Moderate | Severe | Complete |
|---|---|---|---|---|---|
| 8513 | All radicular groups, upper extremity, major / minor | 20% / 20% | 40% / 30% | 70% / 60% | 90% / 80% |
| 8515 | Median nerve, major / minor | 10% / 10% | 30% / 20% | 50% / 40% | 70% / 60% |
| 8521 | Common peroneal nerve, one leg | 10% | 20% | 30% | 40% |
| 8524 | Tibial nerve, one leg | 10% | 20% | 30% | 40% |
| 8526 | Femoral nerve, one leg | 10% | 20% | 30% | 40% |
Source: 38 C.F.R. § 4.124a. Major and minor refer to the dominant and nondominant upper extremity.
Rating Examples for DC 8520
| Criteria Under DC 8520, Sciatic Nerve, One Leg | VA Rating |
|---|---|
| Complete paralysis, with the foot dangling and dropping, no active movement possible below the knee and knee flexion weakened or very rarely lost | 80% |
| Severe incomplete paralysis with marked muscular atrophy | 60% |
| Moderately severe incomplete paralysis | 40% |
| Moderate incomplete paralysis | 20% |
| Mild incomplete paralysis | 10% |
When VA Uses the Wrong Diagnostic Code for CIDP
Sometimes the rating decision does not match the actual nerve distribution shown by the medical evidence. Different nerve codes carry different maximum ratings: a single median nerve code may produce a different result than a code for all radicular groups if the medical evidence supports broader upper-extremity involvement. A CIDP rating decision should be checked for the affected nerve, the extremity, the dominant or nondominant arm, the severity level and whether every affected extremity received the correct evaluation.
The Wholly Sensory Rule
When the evidence documents only pain, numbness, tingling or sensory loss, meaning that the impairment is wholly sensory, the CIDP rating is likely to be that for the mild, or at most, the moderate degree of the condition. An examination that records numbness but does not adequately test strength, reflexes or atrophy can produce a lower evaluation.
A veteran with CIDP needs evidence that shows the full neurological picture: motor weakness, absent reflexes, muscle atrophy, gait impairment, foot drop, loss of grip strength and falls can support a rating that isn’t limited to sensory symptoms alone.
How Neuritis and Neuralgia Affect CIDP Ratings
VA rates neuritis and neuralgia on the same peripheral nerve scales, but 38 C.F.R. § 4.123 and 38 C.F.R. § 4.124 impose ceilings that can affect the rating.
Neuritis characterized by loss of reflexes, muscle atrophy, sensory disturbances and constant pain may be rated up to severe incomplete paralysis. Without the organic changes described in § 4.123, neuritis is generally capped at moderate incomplete paralysis, or moderately severe incomplete paralysis for sciatic nerve involvement.
Neuralgia characterized by dull and intermittent pain in a typical nerve distribution is generally capped at moderate incomplete paralysis. The diagnostic code selected by VA should therefore be checked against the medical findings.
The Bilateral Factor and Its Effect on CIDP Ratings
The bilateral factor can increase the combined evaluation when CIDP causes compensable disability in both arms, both legs or paired skeletal muscles. The VA combines the ratings for the right and left sides and adds 10% of that combined value before continuing the combined rating calculation.
Secondary Conditions to CIDP
Service-connected CIDP can support secondary claims when the disease causes or aggravates additional disability. CIDP can produce severe gait impairment, falls, foot drop, weakness, loss of hand function and other limitations; if they are separately diagnosed they may qualify for secondary service connection if the medical evidence supports the link between them and CIDP.
VA must still avoid pyramiding: the same manifestation cannot be compensated twice under different diagnostic codes. Separate evaluations require distinct disability or impairment. They may be appropriate when the symptoms involve distinct nerve branches and do not overlap.
Winning Additional Compensation
When CIDP affects walking, standing, lifting, carrying, driving, typing, gripping, or attendance and workplace safety, it can make the veteran eligible for Total Disability Based on Individual Unemployability, paid at the 100% VA disability rate (even if the veteran’s combined rating is below 100%). Hill & Ponton assists veterans in winning TDIU.
Severe service-connected CIDP may qualify for Special Monthly Compensation, for instance when CIDP leaves a hand or foot with a loss of function similar to amputation. Aid and attendance is a possibility if service-connected disabilities require regular help with daily activities.
What Evidence Supports a CIDP VA Claim or Appeal?
- A confirmed CIDP diagnosis from a neurologist
- Nerve conduction studies and EMG evidence of demyelination
- Spinal fluid, nerve biopsy or other supporting studies when those studies were performed
- Treatment records showing the course of CIDP and the veteran’s response
- Service records showing the in-service event, injury, disease or exposure
- A reasoned medical nexus opinion for direct or secondary service connection
- A discussion of competing causes, including diabetes, alcohol use, medications, hereditary conditions, age, radiculopathy or other neurological diagnoses
- Lay statements describing when weakness, numbness, clumsiness, balance problems or falls began and how those symptoms progressed
- Functional evidence showing what the veteran can no longer do safely or consistently
- Employment evidence when CIDP affects the ability to work
Get Help With a Denied CIDP VA Disability Claim
CIDP claims can involve several affected nerves, several extremities and several legal theories at the same time. A rating decision may require review of service connection, the selected diagnostic code, severity, bilateral factor, TDIU and Special Monthly Compensation.
Hill & Ponton represents veterans in VA disability appeals, including complex neurological and toxic exposure cases. Veterans whose CIDP claim was denied or underrated can request a free case evaluation to review the available appeal options.
Written by